

PTSD and substance use rarely exist in completely separate boxes. For some men, alcohol or drugs become a way to quiet intrusive memories, stay asleep, blunt anger, or make it through another shift without feeling everything that comes with trauma. Then the substance use creates its own consequences: disrupted sleep, withdrawal, anxiety, relationship problems, and increased reactivity.
That can create a difficult treatment problem. If substance use is addressed without the trauma underneath it, the person may become sober without having the tools to handle what sobriety exposes. If trauma is addressed while active substance use remains uncontrolled, it can be difficult to consistently engage in trauma-focused therapy.
This is why PTSD and addiction treatment often works best when both conditions are addressed as connected problems rather than separate diagnoses. Treating only one condition can leave important drivers of the other unaddressed.
For veterans, firefighters, police officers, EMTs, and other people exposed to repeated traumatic events, the connection can be particularly important. Trauma may involve not only fear but also grief, responsibility, guilt, or moral injury—the psychological impact of actions or experiences that conflict with deeply held values. Moral injury is not itself a psychiatric diagnosis, although it can overlap with PTSD, depression, guilt, shame, and substance use.
The goal is not simply to stop using a substance or eliminate traumatic memories. The goal is to build enough stability to process trauma while developing healthier ways to regulate the nervous system and respond to triggers.
Why sobriety made the flashbacks worse

Getting sober can sometimes feel worse before it feels better.
A person who has been drinking heavily or using drugs to manage trauma may have spent months or years relying on substances for emotional regulation. Alcohol, for example, can temporarily reduce tension and make falling asleep easier. Other substances may create emotional distance from memories or sensations that feel overwhelming.
When that coping mechanism disappears, the underlying distress can become much more noticeable.
This does not mean sobriety caused the PTSD. The trauma was already there. Substance use may simply have been masking, interrupting, or temporarily suppressing some of its effects.
This is where avoidance and numbing become important. Avoiding trauma reminders can provide short-term relief, but it can also prevent someone from learning that those memories and sensations can be tolerated without returning to substance use.
Early recovery can therefore bring increased awareness of:
- Intrusive memories or nightmares
- Irritability and emotional reactivity
- Difficulty concentrating
- Sleep disruption
- Physical tension
- Strong reactions to sounds, smells, places, or situations associated with trauma
- Cravings when distress increases
Without an alternative coping strategy, the brain may interpret this discomfort as evidence that the person needs the substance again.
That is why stabilization matters. A person does not have to choose between sobriety and trauma treatment. Effective care can address both while moving at a clinically appropriate pace.
If trauma is driving your substance use, our trauma treatment program treats both together. Veterans can also read our guide to VA substance abuse treatment.
The loop: hyperarousal, drinking to sleep, rebound
One of the clearest ways to understand co-occurring PTSD and substance use is to look at the cycle rather than either condition in isolation.
Trauma-related hyperarousal can leave the nervous system feeling constantly activated. Someone may feel tense, watchful, restless, angry, or unable to switch off at the end of the day.
Sleep can become especially difficult.
A person may discover that drinking makes it easier to fall asleep. The immediate effect can feel like relief: the body relaxes, thoughts slow down, and emotional intensity temporarily decreases. For some, this pattern can gradually contribute to alcohol addiction when drinking becomes a regular way to manage sleep or emotional distress.
But alcohol changes sleep architecture and can contribute to poorer-quality sleep and nighttime disruption. As its effects wear off, anxiety and physical activation may return. Withdrawal or rebound symptoms can further intensify distress.
The cycle can look like this:
For some people, the cycle can look like this: Trauma reminder → hyperarousal → difficulty sleeping → alcohol or drug use → temporary relief → disrupted sleep/rebound → greater distress → renewed use
This is not simply a matter of lacking willpower.
Research has identified changes in stress-response systems, including the HPA axis, in PTSD and chronic substance use. These systems help regulate the body’s response to stress, but they do not provide a simple explanation for any one person’s symptoms, drinking, drug use, or relapse.
Treatment aims to interrupt the cycle at multiple points.
For example, trauma therapy can address the memories and beliefs driving distress. Medication may help with specific symptoms when clinically appropriate. Addiction treatment can reduce cravings and establish alternatives to substance-based coping.
This is the foundation of trauma-informed addiction treatment: understanding what the substance is doing for the person while helping them develop safer ways to meet the same underlying needs.
Why 90-days-sober-first rules break down
A common treatment assumption is that someone must achieve a long period of sobriety before trauma can be addressed.
There is a reason clinicians may want initial stabilization. Someone experiencing severe withdrawal, uncontrolled intoxication, acute psychiatric symptoms, or an unstable living situation may not be ready for intensive trauma processing.
But a rigid “90 days sober first” rule does not fit every person.
The appropriate timing depends on factors such as:
- Current substance use and withdrawal risk
- Medical and psychiatric stability
- Ability to participate consistently in treatment
- Risk of self-harm or other immediate safety concerns
- Available social support
- Sleep and daily functioning
- Motivation and readiness for trauma work
- The type and intensity of trauma symptoms
Modern dual diagnosis treatment can address substance use and trauma simultaneously without requiring a person to completely resolve one disorder before receiving help for the other.
That does not mean everyone should begin intensive trauma processing immediately. Severe withdrawal, intoxication, acute psychiatric instability, or other safety concerns may require stabilization first.
Instead, substance use care and PTSD care can begin within the same overall treatment plan, while the timing and intensity of trauma-focused work are individualized according to safety, stability, readiness, and clinical assessment.
For someone whose alcohol use is part of the cycle, addiction treatment may include behavioral interventions, peer support, relapse-prevention planning, and—when appropriate—medications such as naltrexone. Naltrexone can reduce the rewarding effects of alcohol and help some people reduce drinking or maintain abstinence.
The point is not to replace one coping mechanism with another. It is to make recovery more manageable while the deeper drivers of substance use are addressed.
If substance use and trauma are interfering with each other, the first step is finding care that can address both rather than forcing you to choose one problem at a time. Explore treatment options through our admissions page.
What integrated dual diagnosis treatment can include
Integrated treatment does not follow one universal calendar. The pace and sequence depend on the person’s symptoms, substance use history, safety, medical needs, readiness, and response to treatment.
A treatment plan may move through overlapping stages such as:
Assessment and stabilization
Early care may focus on safety, withdrawal management when necessary, sleep, nutrition, medical assessment, and understanding the relationship between trauma and substance use. Skyline doesn’t provide detox; if medical withdrawal management is needed, we coordinate with detox partners first.
The treatment team may explore questions such as:
- When do cravings become strongest?
- What situations trigger emotional distress?
- Is substance use primarily connected to sleep, anxiety, anger, memories, or social situations?
- What happens physically and emotionally before and after using?
- What supports are available outside treatment?
The goal is to create enough stability for meaningful therapeutic work.
Building alternatives to substance use
Treatment begins strengthening practical coping skills.
A person may learn grounding techniques, emotional-regulation strategies, craving-management skills, communication tools, and ways to identify triggers before they escalate.
Sleep becomes an important target because exhaustion can make both trauma symptoms and cravings harder to manage.
Medication may also be considered when clinically appropriate.
Trauma-focused treatment when clinically appropriate
When adequate stability and readiness are present, the clinical team may introduce a trauma-focused approach. This timing is individualized rather than tied to a fixed number of sober days or treatment weeks.
This could include EMDR, Cognitive Processing Therapy, Prolonged Exposure, or another evidence-based approach depending on the person’s needs and clinical assessment.
The objective is not to erase the past. It is to change the way the person responds to memories, beliefs, and reminders connected to the trauma.
Consolidation, relapse prevention, and continuing care
As treatment progresses, the focus increasingly shifts toward maintaining gains outside a structured environment.
That may involve identifying high-risk situations, strengthening relationships, creating a continuing-care plan, and preparing for moments when trauma symptoms or cravings return.
Recovery is not measured by never having another trigger.
It is measured by having more choices when a trigger occurs.
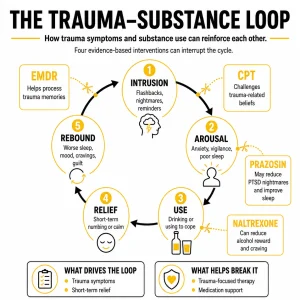
EMDR, CPT, and Seeking Safety in active recovery
Different trauma therapies address different aspects of the trauma-substance relationship.
EMDR, or Eye Movement Desensitization and Reprocessing, is an evidence-based trauma-focused treatment for PTSD. People searching for EMDR for addiction should know that EMDR is not a stand-alone addiction treatment. When trauma and substance use co-occur, it may be delivered alongside evidence-based substance use treatment as part of an integrated plan.
Cognitive Processing Therapy (CPT) takes a different approach. It helps people examine trauma-related beliefs and interpretations that may be keeping them stuck. For someone struggling with guilt, shame, responsibility, or moral injury, examining these beliefs can become an important part of recovery.
Prolonged Exposure focuses on gradually and safely confronting trauma memories and reminders rather than relying on avoidance. It may be appropriate for some people with co-occurring substance use disorders when adequate stability and clinical support are present.
Seeking Safety is a present-focused therapy designed for people dealing with trauma and substance use. It emphasizes coping skills, safety, relationships, boundaries, and managing triggers without requiring detailed trauma processing. It can support stabilization and coping, but current evidence generally favors trauma-focused treatments such as Prolonged Exposure, Cognitive Processing Therapy, or EMDR for reducing PTSD symptoms when those approaches are clinically appropriate.
The right approach depends on the individual.
There is no single therapy that every person with PTSD and addiction should receive, and trauma processing should not be rushed simply because someone is newly sober.
The larger principle is integration: addiction treatment should recognize trauma, and trauma treatment should recognize the realities of recovery from substance use.
Sleep, medication, first responders

Sleep deserves special attention because it can connect nearly every part of the trauma-substance cycle.
Someone who cannot sleep may become more emotionally reactive, physically exhausted, and vulnerable to cravings. If alcohol or another substance has become the person’s primary sleep strategy, removing it without replacing the underlying strategy can create a difficult adjustment period.
Clinicians may use behav